Friday, November 12, 2021

IHE conflicting Patient Identity Feed patterns

Now that IHE has added a PIXm Feed transaction, there is now confusion between PIXm and PMIR. Let me explain.

Overall
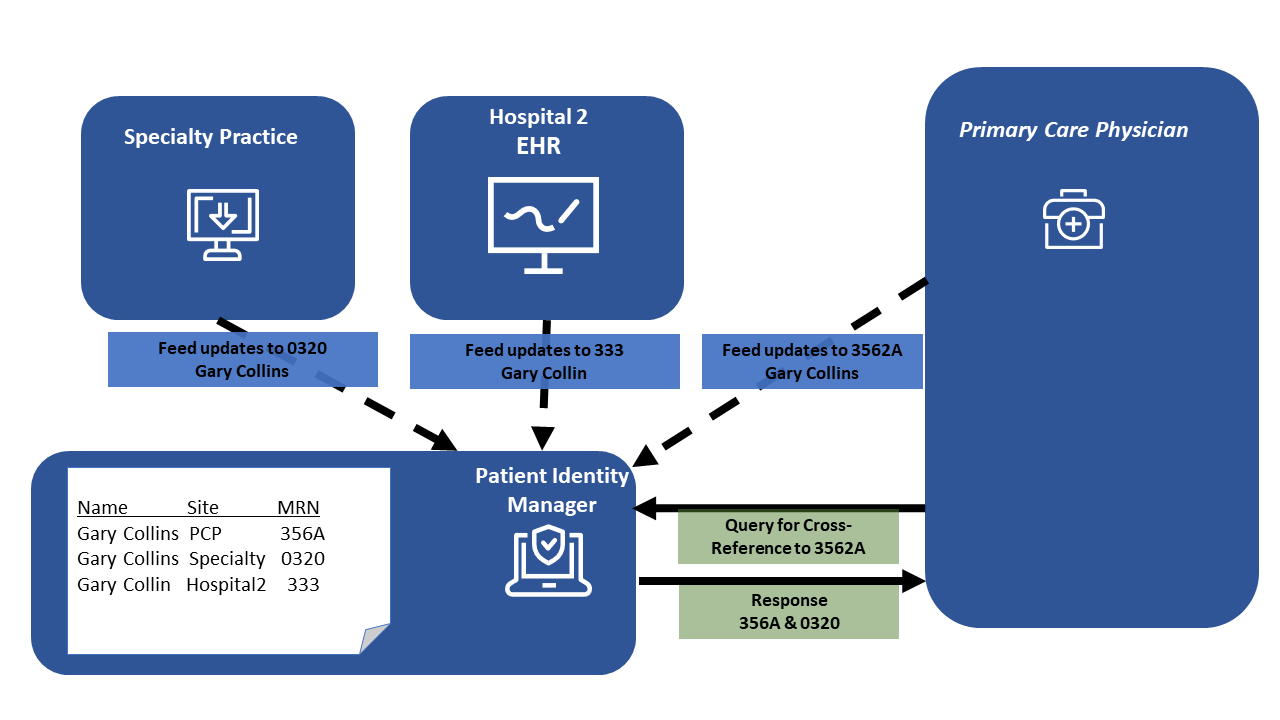
The PIXm and PMIR implementation guides are intending on solving two very different models of managing Patient Identity. There is no expectation that a community would deploy both models.

This is further explained in the "HIE Whitepaper - Patient Identity Management"

PMIR

PMIR model is one where a community wants to cooperate on a master Patient identity for each patient, a "golden" patient. This model has each authoritative party in the community cooperatively keeping the single Patient identity for a patient up-to-date. When a patient is seen one of the locations in the community, the master Patient identity is pulled from the PMIR Registry. If there is anything that needs to be updated, then that system will send the update back to the PMIR Registry. Thus there is only one Patient identity (demographics, addresses, phone numbers, national numbers, etc). This cooperation is what PMIR is all about.

There are additional features in PMIR that enable those that rely on this master Patient instance to be notified of changes. This is another use of the feed. This feed does enable the data custodians to be notified of important changes like when two master identifiers were determined to actually be about the same patient and thus have been merged. In this case the data custodian is expected properly update their data to represent the merge.

PIXm 

PIXm model is one where a community wants to cooperate on Cross-References between each community members instance of the Patient identity as they know it. Where a cross-reference is simply a list of  Patient.id and Patient.identifier (that is a patient identity such as MRN). The cross-reference is derived at using the other elements in the Patient resource, but a cross-reference does not expose on a query interface these other elements in the Patient resource. The PIXm query is just a set of identifiers (id and identifier) that are cross-referenced. 

Each time a community participant updates their local instance of the Patient identity, they do feed those updates to the PIXm Manager. The Manager looks at the details with the ONLY output that the PIXm Manager updates the cross-references that it would return in the future when a PIXm client asks for the cross-references. It is very likely that the PIXm Manager does remember the demographics, addresses, phone numbers, national numbers, etc... but there is no effort to harmonize these at the element level. 

PMIR uses PIXm

PMIR does include the PIXm Query transaction. This is useful when a client in the PMIR environment for a very few cases:

1. When the client does not want the whole Patient, just the .id so that it can record that value. There are plenty of client use-cases where it is not important to have access to the full, and sometimes sensitive, elements in the Patient resource. For example a weight scale wanting to record a new body-weight observation, where the scale knows the PMIR Registry and knows that the weight scale GUID is recorded as a Patient.identifier. Thus this device can do a PIXm Query given the scale GUID and get the Patient .id value. It can put that value into the Observation.subject element. 

2. When the client does not want the whole Patient, just knows the Patient .id and wants a local MRN value. Not as clear why this client does not want to be exposed to the Patient Demographics, but it is possible.

PIXm and PMIR feed are not compatible

So the above should make it clear that PIXm and PMIR are solving different community models, and that those models would not exist in the same community. It is possible that a PMIR community would want to be a community participating in a broader PIXm community. Thus the PMIR Registry would participate as a PIXm Patient Identity Source.

The elephant in the room is... WHY did PIXm and PMIR feed choose totally different technical approaches at the FHIR interaction? If you didn't notice this, let me explain.

  • PMIR uses a "history" Bundle for the Feed. 
  • PIXm uses more basic RESTful Create/Update/Delete (mostly)
Neither model is great. It is very possible that in the spring we update PMIR to more closely align with PIXm. I say "more closely" because the "expected actions" of the PMIR Registry are very different than the those of the PIXm cross-reference Manager. But the communication on the wire might be possible to be 'closer'...

Trial-Implementation

All this said... these implementation guides are both in "Trial-Implementation" state. This is the state used when IHE wants implementers to try it out, and give feedback to improve the future. So, please try them out, and give us feedback. Would prefer you join the ITI-Technical committee, but would also take input on the Public-Comment forum or GitHub for PIXm. I would also welcome comments on this blog article.

Thursday, November 11, 2021

My Father

My father passed away this week, joining my mother. His health has been fading since his love of 70 years passed. He passed peacefully with his favorite nurse at his side, in the middle of the night.  

During my life he was a Wisconsin State Trooper. He joined on a dare from his older brother who had joined in 1956, the next year my father joined the 6th recruit Class, badge #287.  He retired after 28 years. There were plenty of stories of my father as a Trooper. Most of what I remember is that he had friends in every little city, truck-stop, gas-station, etc. I never caught the skill of making friends that he had. 


I learned from my father (and mother) respect for others. I know that police do not have a good reputation today, and I suspect there were bad apples back then too. But I am confident of the stories I was taught regarding "perspective". I was taught to not judge someone by the first impression, to try very hard to look at their situation from their perspective. It is when you see their perspective you realize they are fighting trying times. This perspective exercise is what enables me to be comfortable with people that are "not like me", people who make life choices that I myself can't understand, people who are down on their luck and likely would benefit greatly from the smallest of help. Perspective is key, try to walk a mile in their shoes before you judge. 

I learned from my father work-ethic. He would work hard when doing a job, with appropriate breaks. But he would also reserve recreation time. And of course sleep.  He enjoyed odd-jobs, such as gathering up used tires to take them to the "re-tread" factory. We would fill the back of the pickup truck, nicely organized tires, three rows high. Learning how to get the rain water out of the tire without getting wet. I am sure this odd-job was never worth the income.

When I heard of his passing, I was relieved for him. I will miss the bi-weekly visits I had with him. I went for a walk, turned on classical music (my mothers favorite) and listened for sour-notes and clinkers (my father always would). Ended up sitting in a local church prayer garden, alone with the sunset.


Wednesday, November 10, 2021

Updates to IHE foundational #FHIR profiles MHD, PDQm, and PIXm

Updated MHD, PDQm, and PIXm

Patient Identifier Cross-reference for Mobile (PIXm) -


Rev. 3.0.0. This revision was created using the Implementation Guide publisher. This is an update of PIXm that was previously published in PDF form. This new publication is published in HTML form with a full set of conformance resources and examples. New functionality has been added to support a patient identity feed to inform the Patient Identity Manager of changes to patient identities.

https://profiles.ihe.net/ITI/PIXm/index.html


Patient Demographics Query for Mobile (PDQm) - Rev. 2.3.0. This revision was created using the Implementation Guide publisher. This is an update of PDQm that was previously published in PDF form. This new publication is published in HTML form with a full set of conformance resources and examples. No new features were added.

https://profiles.ihe.net/ITI/PDQm/index.html


Mobile Access to Health Documents (MHD) - Rev. 4.0.2. This revision updated the publication to use the new Implementation Guide template. No new functionality was added.

https://profiles.ihe.net/ITI/MHD/index.html


Mobile Care Services Discovery (mCSD) Use Cases White Paper - Rev. 1.1 . This white paper presents multiple use cases that mCDS supports.

https://profiles.ihe.net/ITI/papers/mCSD/index.html


IHE Publications

These new publications are a part of the IHE family of Implementation Guide Profiles, and can be found at https://profiles.ihe.net

IHE is dedicated to the task of use-case driven Implementation Guide authoring, publication, maintenance, and testing. There is a long list of IHE Profiles (a form of Implementation Guide) supporting Healthcare IT workflows within and across the Healthcare space.


IHE Connectathon

These updated Implementation Guides will be available for formal product Interoperability testing at the upcoming IHE Connectathons https://www.ihe.net/participate/connectathon. 


Tuesday, October 26, 2021

IHE IT-Infrastructure fall 2021

IHE ITI Tech met last week and had a very productive meeting. It seems we are getting the hang of virtual meetings. I will say that they are still about 50% as productive as a face-to-face. There are times at which we are more productive, but there are times when the virtualness gets in the way. This can be due to the lack of non-verbal queues (oh, you really didn't understand what I said), or inability to stand up and draw a picture on a whiteboard, or because everyone is multi-tasking.

Finished this meeting: (will take a week or two to be actually published on https://profiles.ihe.net )

  • mCSD Whitepaper 
  • PIXm in IG format with Feed transaction - for Trial Implementation
  • PDQm in IG format - for Trial Implementation
Continuing Work Items:
  • Quality improvements to the HTML publication of the Technical Framework publications
  • Maintenance (CP)
  • MHD to a Federation task-142
New Work Items:
  • Convert mCSD to IG Publisher task-151
  • Create Implementation Guide Profile ATNA auditEvent patterns for generic FHIR RESTful transactions with pattern informing IHE profile further specializing task-144
  • Convert Metadata Handbook to html publication without technical changes task-169
  • Convert MHDS to html publication without technical changes (not an IG yet) task-166 
Ill cover these in other articles.

Thursday, October 14, 2021

Security of #FHIR implementations concerns

Security Report: "The New Healthcare Ecosystem will depend on FHIR APis, but Are They Secure?"

Alissa Knight did some invited and funded cyberSecurity research and found some good and some bad. No-one should be surprised by that conclusion. The point we should take from this research is that 

  1. EHRs are doing a good job of securing their FHIR implementations
  2. FHIR is good and worthy
  3. There is room for improvement in some implementations 
  4. There are included recommended improvements. 

Some have take a very negative view of the research, most of this negativity is unfounded and driven by the fact that Alissa is excellent at marketing and drama. She has excellent presentation skills, excellent writing skills, excellent hacking skills, and excellent artwork. 

This research was funded by a vendor that provides security frontend for APIs, so certainly there should be some consideration here. I, however, have good reason to believe that this funding did not influence the research. Alissa has a couple of decades of proving she knows what she is doing. This is not just fake research complaining about products that didn't use the vendors solution. Yes there is one mention that a product that did use that vendor solution was not found vulnerable, yes the vendor got mention at the bottom of the report for funding it.

This was not an attempt to bring down FHIR, but rather to challenge us all to be better.  This report says nothing negative about the FHIR standard, it was focused on implementations. 

There is some bad news, some implementations were specifically disgustingly bad at securing the data, and they had lots of data (aggregators). These services had signed up to be part of this research. They were informed of the problems. The report was expressing the trend, not the specific details. Alissa addressed this during the YouTube below, and also on twitter later.

Alissa hosted a Ask Me Anything on live YouTube, the recording here


Deeper dive

The report stands alone, and I have tried to come up with better ways to say what it says, but I just can't. The things that Alissa found were very remedial cyber security issues. Editing URLs in the browser to try to get at obvious other information. Using legitimate security tokens for things it was not intended to do. ...  Alissa has so much deeper skills that she simply never needed to rely on. She goes into all of these details about as detailed as is reasonable without naming products. 

Page 16 was critical for me. I literally was stunned. Not an exaggeration. I knew that there would likely be mistakes, hence why above I said we all should not be surprised she found issues. It was clear there would be issues found. But the class of issues found are just unexplainable.  All of the issues failed to implement even the FIRST section on the FHIR Security page.

Data Aggregators were the worst offenders in my view. I know they provide a useful service, but they do it in ways that are not transparent, and they clearly don't take their responsibility seriously. They have been around for decades, so likely these same bad security implementations were just as bad on their previous proprietary "secret" APIs. The use of FHIR just makes them more obviously bad.

The last bullet on page 16 was the worse, quote:
With one patient engagement app, the API endpoint sent me all the patient and clinician records in its database, indicating it was using the mobile app to filter out just my record.
NO WAY!!??? yup, that happened

mic drop

Conclusion:

I need to bring this back to positives... FHIR is good, the EHRs are good, many apps and services are good... but some are really NOT.  

FHIR is a building block. It has so much to give to us humans (and animals). It will enable many things while it transitions from a "Standard for Trial Use" to something that is used to build CarePlans, Patient Engagement, Emergency Medicine, Disaster Management, Public Health, Artificial Intelligent clinical decision support aids, world wide COVID-19 tracking, and COVID-19 vaccine credentials...  helping patients stay healthy rather than get unhealthy in the first place ...

FHIR is built upon http RESTful concepts, Document concepts, and messaging. These platforms have security and privacy layers available to be used. Healthcare does not need to invent security, we just need to implement it properly. Mostly apply the security layer to the interactions following good policies. Have bad policy, is bad. Have bad implementations, is bad. Have no security, is bad.

All systems that have access to health data need to be designed from the beginning with Privacy Principles which include Security and Security which is about (protecting risks to Confidentiality, Integrity, and Availability).  Failing at "Access Control" makes me wonder about all the other opportunities to have forgotten Privacy and Security in the design.

Now is a good time to be reminded. We are not too far gone, we can do the right thing.

FHIR is the right standard to work with. 

Others comments


Thursday, September 9, 2021

#FHIR Basic AuditEvent for generic RESTful actions

I have drafted a prototype Implementation Guide covering the AuditEvent profiling for generic FHIR RESTful actions.

For any FHIR REST operation there is a well-defined AuditEvent specified in this implementation guide. The appropriate AuditEvent shall be recorded by Client and Server applications that claim conformance to this implementation guide. The resulting set of AuditEvents are made available to a client authorized to retrieve them. The AuditEvent in this case is useful for the typical privacy office and security office use, but is also useful to enable a Patient facing app that can inform the patient when and how their data are used.

Basic Auditing where there is a known subject of the data involved. This profile is a formal specification of the guidance given in the FHIR Core AuditEvent under Common Scenarios

This guide does not cover all AuditEvents. It does not cover
  • how accesses to data where their is no subject, such as a Provider Directory. Although this is likely similar, just without the mandated Patient entity.
  • how failures are recorded. Failures are recorded with the .outcome that is not success, and is thus a very large body of possibilities. Failures are logged with best-effort and with verbose content. This makes the AuditEvent of a failure very hard to characterize, vary hard to automatically process, and possibly exposing of privacy or business secrets. These might be access control denials, which the patient would be interested in but for which it is not clear they would be due these kinds of notices. These might be infrastructural failures, which are too hard to characterize.
The AuditEvent profiles here could be used as a prototype for a more specific AuditEvent profile in a use-case specific Implementation Guide. Where a use-case specific Implementation Guide defines an AuditEvent profile, those profiles should be used rather than the Basic AuditEvent profiles found here. Both could be recorded without harm. 

Actors defined in the Implementation Guide


Data using Client

Requesting application in a REST relationship with the Server.

Note that the Client may also record the appropriate AuditEvent into the Audit-Repository. For security use-cases it is very helpful for the client to record the AuditEvent too, as this sets up a pattern of normal operation that can be watched for deviations. Deviations such as the client stopping audit logging should be investigated, a possible cause is that the client credentials have been stolen and are being used by another application than the one authorized.

Data Server

Responding server that holds the data the Client is requesting thru REST. Server records the appropriate AuditEvent into the Audit-Repository.

Audit Repository

FHIR repository holding the AuditEvents created, and provides access to the AuditEvents to Audit-Clients. The Audit-Repository would typically not allow Update or Delete of any AuditEvent previously recorded. Thus only allowing Create, and Read of AuditEvents.

Note that the Audit-Repository may be the same system as the Server.

Audit using Client

A Client that retrieves AuditEvents for some functionality. Where the functionality is not constrained or defined here. The Audit-Client queries AuditEvents for a given Patient.

Purpose

The reason for me to have written this Implementation Guide is for two specific reasons
  1. To provide a structureDefinition Profile set of these basic audit even patterns. Which does test the FHIR core AuditEvent specification.
  2. To provide a pattern for an Audit using Client that uses the AuditEvent(s) for various purposes. Including the purpose of providing a  Patient Engagement - Access Log

References

Monday, August 16, 2021

FHIR Document Digital Signatures

I was asked about Digital Signatures for FHIR documents:

I am working on _____  IG that is FHIR document based and we need a means to prove authenticity. The model is relatively simple in that a document and all of its parts represent a single thing that needs to be “signed”.

I have looked around for examples of this in IGs and in example documents and I have not found anything. I see a lot of references to CDA documents and signatures, but not much in the ay of FHIR documents. Can you point me in the right direction? Are there example FHIR IGs and documents out there. Where should I start?

Documents are good

The right way to do this is to have the signature cover the whole document, you have gotten to that point well. This is important as the signature covers all of the contents, including identity, date/time, context, etc; and also the meat of the content you are needing signed.  The point here is that a Document does not rely on references to outside data that might change, but rather a document should copy within itself everything that needs to be protected with the signature.

A FHIR-Document is not different than a CDA Document or any other kind of document. It is seen by the digital signature as simply a bucket of bits. Thus anything you see showing a digital signature on a CDA document is likely just as applicable to a FHIR-Document. 

The wrong way to do this is to believe that one can include a signature within the document (or within anything that is signed -- for example a FHIR Resource that contains a signature element). As soon as you need to exclude something in the bucket of bits, you open up the opportunity for other things to be excluded from the signature. So, always sign a whole bucket of bits, and a whole bucket of bits that is internally complete (doesn't rely on outside data).

The solution

A signature over a document is a document itself. It is a document of type XML-Signature.

There is already a specification for this from IHE – Document Digital Signature (DSG); and is what the FHIR core specification recommends. https://profiles.ihe.net/ITI/TF/Volume1/ch-37.html

Both documents would have DocumentReference that point at the bits (My preference is using a Binary, but the enclosed base64 data is an alternative).

The two documents would have a relationship. The digital signature (DocumentReference) would have a .relatesTo with the .relatesTo.target of the DocumentReference with the content; and the .relatesTo.code of ‘signs’.

Some more context on this https://healthcaresecprivacy.blogspot.com/2017/04/ihe-document-digital-signature-dsg.html

Note the concept of having everything needed (document) in one blob to be signed is very similar to what the COVID-19 credential does, but they strip things down to the bare minimum in order to fit in a reasonable QR code. They do use a JSON signature and encapsulate the content. So it is logically similar to the above, but practically it looks very different.  (Updated to be more correct)

My other articles on Digital Signatures